
NEET MDS Lessons
Orthodontics
Wire Characteristics
- Resilience: Area under stress-strain curve up to proportional limit; energy storage capacity
- Formability: Permanent deformation before failure
- Ideal wire properties: High strength, low stiffness, high range, high formability
- Nomograms: Developed by Kusy for wire comparison
- Shape memory & superelasticity: Unique to NiTi alloys
Wire Types & Inventors
| Wire Type | Inventor/Details |
|---|---|
| NiTi | William F. Buehler (1962), George Andreasen (1970) |
| Cu-NiTi | Rohit Sachdeva; quaternary alloy |
| Beta Titanium (TMA) | Charles Burstone; Titanium-Molybdenum-Aluminium |
| Stainless Steel | Bearley; 18-8 composition |
| Elgiloy | Cobalt-Chromium alloy; heat-treated for strength |
Elgiloy Color Coding
| Type | Color |
|---|---|
| Soft | Blue |
| Ductile | Yellow |
| Semi-resilient | Green |
| Resilient | Red |
Metallurgical Concepts
- Passivation: Cr₂O₃ layer from chromium prevents corrosion
- Sensitization: Loss of passivation due to chromium carbide formation (400 – 900° C)
- Cold working: Increases hardness/strength, decreases elongation
- Annealing: Reverses strain hardening; temp = 1/2 melting point
Camouflage in orthodontics refers to the strategic use of orthodontic treatment to mask or disguise underlying skeletal discrepancies, particularly in cases where surgical intervention may not be feasible or desired by the patient. This approach aims to improve dental alignment and occlusion while minimizing the appearance of skeletal issues, such as Class II or Class III malocclusions.
Key Concepts of Camouflage in Orthodontics
-
Objective:
- The primary goal of camouflage is to create a more aesthetically pleasing smile and functional occlusion without addressing the underlying skeletal relationship directly. This is particularly useful for patients who may not want to undergo orthognathic surgery.
-
Indications:
- Camouflage is often indicated for:
- Class II Malocclusion: Where the lower jaw is positioned further back than the upper jaw.
- Class III Malocclusion: Where the lower jaw is positioned further forward than the upper jaw.
- Mild to Moderate Skeletal Discrepancies: Cases where the skeletal relationship is not severe enough to warrant surgical correction.
- Camouflage is often indicated for:
-
Mechanisms:
- Tooth Movement: Camouflage typically involves
moving the teeth into positions that improve the occlusion and facial
aesthetics. This may include:
- Proclination of Upper Incisors: In Class II cases, the upper incisors may be tilted forward to improve the appearance of the bite.
- Retroclination of Lower Incisors: In Class III cases, the lower incisors may be tilted backward to help achieve a better occlusal relationship.
- Use of Elastics: Orthodontic elastics can be employed to help correct the bite and improve the overall alignment of the teeth.
- Tooth Movement: Camouflage typically involves
moving the teeth into positions that improve the occlusion and facial
aesthetics. This may include:
-
Treatment Planning:
- A thorough assessment of the patient's dental and skeletal
relationships is essential. This includes:
- Cephalometric Analysis: To evaluate the skeletal relationships and determine the extent of camouflage needed.
- Clinical Examination: To assess the dental alignment, occlusion, and any functional issues.
- Patient Preferences: Understanding the patient's goals and preferences regarding treatment options.
- A thorough assessment of the patient's dental and skeletal
relationships is essential. This includes:
Advantages of Camouflage
- Non-Surgical Option: Camouflage provides a way to improve dental alignment and aesthetics without the need for surgical intervention, making it appealing to many patients.
- Shorter Treatment Time: In some cases, camouflage can lead to shorter treatment times compared to surgical options.
- Improved Aesthetics: By enhancing the appearance of the smile and occlusion, camouflage can significantly boost a patient's confidence and satisfaction.
Limitations of Camouflage
- Not a Permanent Solution: While camouflage can improve aesthetics and function, it does not address the underlying skeletal discrepancies, which may lead to long-term issues.
- Potential for Relapse: Without proper retention, there is a risk that the teeth may shift back to their original positions after treatment.
- Functional Complications: In some cases, camouflage may not fully resolve functional issues related to the bite, leading to potential discomfort or wear on the teeth.
Growth is the increase in size It may also be defined as the normal change in the amount of living substance. eg. Growth is the quantitative aspect and measures in units of increase per unit of time.
Development
It is the progress towards maturity (Todd). Development may be defined as natural sequential series of events between fertilization of ovum and adult stage.
Maturation
It is a period of stabilization brought by growth and development.
CEPHALOCAUDAL GRADIENT OF GROWTH
This simply means that there is an axis of increased growth extending from the head towards feet. At about 3rd month of intrauterine life the head takes up about 50% of total body length. At this stage cranium is larger relative to face. In contrast the limbs are underdeveloped.
By the time of birth limbs and trunk have grown faster than head and the entire proportion of the body to the head has increased. These processes of growth continue till adult.
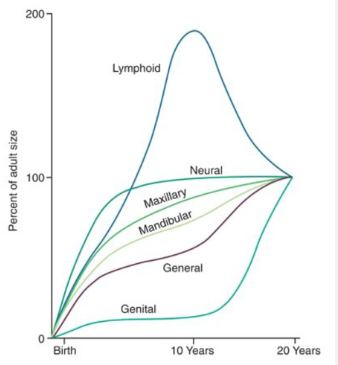
SCAMMON’S CURVE
In normal growth pattern all the tissue system of the body do not growth at the same rate. Scammon’s curve for growth shows 4 major tissue system of the body;
• Neural
• Lymphoid
• General: Bone, viscera, muscle.
• Genital
The graph indicates the growth of the neural tissue is complete by 6-7 year of age. General body tissue show an “S” shaped curve with showing of rate during childhood and acceleration at puberty. Lymphoid tissues proliferate to its maximum in late childhood and undergo involution. At the same time growth of the genital tissue accelerate rapidly.
Nail Biting Habits
Nail biting, also known as onychophagia, is one of the most common habits observed in children and can persist into adulthood. It is often associated with internal tension, anxiety, or stress. Understanding the etiology, clinical features, and management strategies for nail biting is essential for addressing this habit effectively.
Etiology
-
Emotional Problems:
- Persistent nail biting may indicate underlying emotional issues, such as anxiety, stress, or tension. It can serve as a coping mechanism for dealing with these feelings.
-
Psychosomatic Factors:
- Nail biting can be a psychosomatic response to stress or emotional discomfort, manifesting physically as a way to relieve tension.
-
Successor of Thumb Sucking:
- For some children, nail biting may develop as a successor to thumb sucking, particularly as they transition from one habit to another.
Clinical Features
-
Dental Effects:
- Crowding: Nail biting can contribute to dental crowding, particularly if the habit leads to changes in the position of the teeth.
- Rotation: Teeth may become rotated or misaligned due to the pressure exerted during nail biting.
- Alteration of Incisal Edges: The incisal edges of the anterior teeth may become worn down or altered due to repeated contact with the nails.
-
Soft Tissue Changes:
- Inflammation of Nail Bed: Chronic nail biting can lead to inflammation and infection of the nail bed, resulting in redness, swelling, and discomfort.
Management
-
Awareness:
- The first step in management is to make the patient aware of their nail biting habit. Understanding the habit's impact on their health and appearance can motivate change.
-
Addressing Emotional Factors:
- It is important to identify and treat any underlying emotional issues contributing to the habit. This may involve counseling or therapy to help the individual cope with stress and anxiety.
-
Encouraging Outdoor Activities:
- Engaging in outdoor activities and physical exercise can help reduce tension and provide a positive outlet for stress, potentially decreasing the urge to bite nails.
-
Behavioral Modifications:
- Nail Polish: Applying a bitter-tasting nail polish can deter nail biting by making the nails unpalatable.
- Light Cotton Mittens: Wearing mittens or gloves can serve as a physical reminder to avoid nail biting and can help break the habit.
-
Positive Reinforcement:
- Encouraging and rewarding the individual for not biting their nails can help reinforce positive behavior and motivate them to stop.
Myofunctional Appliances
- Myofunctional appliances are removable or fixed devices that aim to correct dental and skeletal discrepancies by promoting proper oral and facial muscle function. They are based on the principles of myofunctional therapy, which focuses on the relationship between muscle function and dental alignment.
-
Mechanism of Action:
- These appliances work by encouraging the correct positioning of the tongue, lips, and cheeks, which can help guide the growth of the jaws and the alignment of the teeth. They can also help in retraining oral muscle habits that may contribute to malocclusion, such as thumb sucking or mouth breathing.
Types of Myofunctional Appliances
-
Functional Appliances:
- Bionator: A removable appliance that encourages forward positioning of the mandible and helps in correcting Class II malocclusions.
- Frankel Appliance: A removable appliance that modifies the position of the dental arches and improves facial aesthetics by influencing muscle function.
- Activator: A functional appliance that promotes mandibular growth and corrects dental relationships by positioning the mandible forward.
-
Tongue Retainers:
- Devices designed to maintain the tongue in a specific position, often used to correct tongue thrusting habits that can lead to malocclusion.
-
Mouthguards:
- While primarily used for protection during sports, certain types of mouthguards can also be designed to promote proper tongue posture and prevent harmful oral habits.
-
Myobrace:
- A specific type of myofunctional appliance that is used to correct dental alignment and improve oral function by encouraging proper tongue posture and lip closure.
Indications for Use
- Malocclusions: Myofunctional appliances are often indicated for treating Class II and Class III malocclusions, as well as other dental alignment issues.
- Oral Habits: They can help in correcting harmful oral habits such as thumb sucking, tongue thrusting, and mouth breathing.
- Facial Growth Modification: These appliances can be used to influence the growth of the jaws in growing children, promoting a more favorable dental and facial relationship.
- Improving Oral Function: They can enhance functions such as chewing, swallowing, and speech by promoting proper muscle coordination.
Advantages of Myofunctional Appliances
- Non-Invasive: Myofunctional appliances are generally non-invasive and can be a more comfortable option for patients compared to fixed appliances.
- Promotes Natural Growth: They can guide the natural growth of the jaws and teeth, making them particularly effective in growing children.
- Improves Oral Function: By retraining oral muscle function, these appliances can enhance overall oral health and function.
- Aesthetic Appeal: Many myofunctional appliances are less noticeable than traditional braces, which can be more appealing to patients.
Limitations of Myofunctional Appliances
- Compliance Dependent: The effectiveness of myofunctional appliances relies heavily on patient compliance. Patients must wear the appliance as prescribed for optimal results.
- Limited Scope: While effective for certain types of malocclusions, myofunctional appliances may not be suitable for all cases, particularly those requiring significant tooth movement or surgical intervention.
- Adjustment Period: Patients may experience discomfort or difficulty adjusting to the appliance initially, which can affect compliance.
Frankel appliance is a functional orthodontic device designed to guide facial growth and correct malocclusions. There are four main types: Frankel I (for Class I and Class II Division 1 malocclusions), Frankel II (for Class II Division 2), Frankel III (for Class III malocclusions), and Frankel IV (for specific cases requiring unique adjustments). Each type addresses different dental and skeletal relationships.
The Frankel appliance is a removable orthodontic device that plays a crucial role in the treatment of various malocclusions. It is designed to influence the growth of the jaw and dental arches by modifying muscle function and promoting proper alignment of teeth.
Types of Frankel Appliances
-
Frankel I:
- Indications: Primarily used for Class I and Class II Division 1 malocclusions.
- Function: Helps in correcting overjet and improving dental alignment.
-
Frankel II:
- Indications: Specifically designed for Class II Division 2 malocclusions.
- Function: Aims to reposition the maxilla and improve the relationship between the upper and lower teeth.
-
Frankel III:
- Indications: Used for Class III malocclusions.
- Function: Encourages forward positioning of the maxilla and helps in correcting the skeletal relationship.
-
Frankel IV:
- Indications: Suitable for open bites and bimaxillary protrusions.
- Function: Focuses on creating space and improving the occlusion by addressing specific dental and skeletal issues.
Key Features of Frankel Appliances
-
Myofunctional Design: The appliance is designed to utilize the forces generated by muscle function to guide the growth of the dental arches.
-
Removable: Patients can take the appliance out for cleaning and during meals, which enhances comfort and hygiene.
-
Custom Fit: Each appliance is tailored to the individual patient's dental anatomy, ensuring effective treatment.
Treatment Goals
-
Facial Balance: The primary goal of using a Frankel appliance is to achieve facial harmony and balance by correcting malocclusions.
-
Functional Improvement: It promotes the establishment of normal muscle function, which is essential for long-term dental health.
-
Arch Development: The appliance aids in the development of the dental arches, providing adequate space for the eruption of permanent teeth.
Types of Springs
In orthodontics, various types of springs are utilized to achieve specific tooth movements. Each type of spring has unique characteristics and applications. Below are a few examples of commonly used springs in orthodontic appliances:
1. Finger Spring
- Construction: Made from 0.5 mm stainless steel wire.
- Components:
- Helix: 2 mm in diameter.
- Active Arm: The part that exerts force on the tooth.
- Retentive Arm: Helps retain the appliance in place.
- Placement: The helix is positioned opposite to the direction of the intended tooth movement and should be aligned along the long axis of the tooth, perpendicular to the direction of movement.
- Indication: Primarily used for mesio-distal movement of teeth, such as closing anterior diastemas.
- Activation: Achieved by opening the coil or moving the active arm towards the tooth to be moved by 2-3 mm.
2. Z-Spring (Double Cantilever)
- Construction: Comprises two helices of small diameter, suitable for one or more incisors.
- Positioning: The spring is positioned perpendicular to the palatal surface of the tooth, with a long retentive arm.
- Preparation: The Z-spring needs to be boxed in wax prior to acrylization.
- Indication: Used to move one or more teeth in the same direction, such as proclining two or more upper incisors to correct anterior tooth crossbites. It can also correct mild rotation if only one helix is activated.
- Activation: Achieved by opening both helices up to 2 mm at a time.
3. Cranked Single Cantilever Spring
- Construction: Made from 0.5 mm wire.
- Design: The spring consists of a coil located close to its emergence from the base plate. It is cranked to keep it clear of adjacent teeth.
- Indication: Primarily used to move teeth labially.
4. T Spring
- Construction: Made from 0.5 mm wire.
- Design: The spring consists of a T-shaped arm, with the arms embedded in acrylic.
- Indication: Used for buccal movement of premolars and some canines.
- Activation: Achieved by pulling the free end of the spring toward the intended direction of tooth movement.
5. Coffin Spring
- Construction: Made from 1.2 mm wire.
- Design: Consists of a U or omega-shaped wire placed in the midpalatal region, with a retentive arm incorporated into the base plates.
- Retention: Retained by Adams clasps on molars.
- Indication: Used for slow dentoalveolar arch expansion in patients with upper arch constriction or in cases of unilateral crossbite.