
NEET MDS Lessons
Orthodontics
- Types: Petit, Delaire
- Reverse pull headgear = Facemask
- Force direction: Downward & backward
- Hooks location: Canine-primary molar area
- Wear duration: 12 – 14 hrs/day
- Natural implants: Primary canines
- Relapse rate: 25 – 30%
- Successful RME activation: Midline diastema
- Force by RME: 10 – 20 lbs
- Force by slow expansion: 2 – 4 lbs
- Quadhelix skeletal:dental expansion: 1:2
Lip Bumper
A lip bumper is an orthodontic appliance designed to create space in the dental arch by preventing the lips from exerting pressure on the teeth. It is primarily used in growing children and adolescents to manage dental arch development, particularly in cases of crowding or to facilitate the eruption of permanent teeth. The appliance is typically used in the lower arch but can also be adapted for the upper arch.
Indications for Use
-
Crowding:
- To create space in the dental arch for the proper alignment of teeth, especially when there is insufficient space for the eruption of permanent teeth.
-
Anterior Crossbite:
- To help correct anterior crossbites by allowing the anterior teeth to move into a more favorable position.
-
Eruption Guidance:
- To guide the eruption of permanent molars and prevent them from drifting mesially, which can lead to malocclusion.
-
Preventing Lip Pressure:
- To reduce the pressure exerted by the lips on the anterior teeth, which can contribute to dental crowding and misalignment.
-
Space Maintenance:
- To maintain space in the dental arch after the premature loss of primary teeth.
Design and Features
-
Components:
- The lip bumper consists of a wire framework that is typically made
of stainless steel or other durable materials. It includes:
- Buccal Tubes: These are attached to the molars to anchor the appliance in place.
- Arch Wire: A flexible wire that runs along the buccal side of the teeth, providing the necessary space and support.
- Lip Pad: A soft pad that rests against the lips, preventing them from exerting pressure on the teeth.
- The lip bumper consists of a wire framework that is typically made
of stainless steel or other durable materials. It includes:
-
Customization:
- The appliance is custom-fitted to the patient’s dental arch to ensure comfort and effectiveness. Adjustments can be made to accommodate changes in the dental arch as treatment progresses.
Mechanism of Action
-
Space Creation:
- The lip bumper creates space in the dental arch by pushing the anterior teeth backward and allowing the posterior teeth to erupt properly. The lip pad prevents the lips from applying pressure on the anterior teeth, which can help maintain the space created.
-
Guiding Eruption:
- By maintaining the position of the molars and preventing mesial drift, the lip bumper helps guide the eruption of the permanent molars into their proper positions.
-
Facilitating Growth:
- The appliance can also promote the growth of the dental arch, allowing for better alignment of the teeth as they erupt.
Late mandibular growth refers to the continued development and growth of the mandible (lower jaw) that occurs after the typical growth spurts associated with childhood and adolescence. While most of the significant growth of the mandible occurs during these early years, some individuals may experience additional growth in their late teens or early adulthood. Understanding the factors influencing late mandibular growth, its implications, and its relevance in orthodontics and dentistry is essential.
Factors Influencing Late Mandibular Growth
-
Genetics:
- Genetic factors play a significant role in determining the timing and extent of mandibular growth. Family history can provide insights into an individual's growth patterns.
-
Hormonal Changes:
- Hormonal fluctuations, particularly during puberty, can influence growth. Growth hormone, sex hormones (estrogen and testosterone), and other endocrine factors can affect the growth of the mandible.
-
Functional Forces:
- The forces exerted by the muscles of mastication, as well as functional activities such as chewing and speaking, can influence the growth and development of the mandible.
-
Environmental Factors:
- Nutritional status, overall health, and lifestyle factors can impact growth. Adequate nutrition is essential for optimal skeletal development.
-
Orthodontic Treatment:
- Orthodontic interventions can influence mandibular growth patterns. For example, the use of functional appliances may encourage forward growth of the mandible in growing patients.
Clinical Implications of Late Mandibular Growth
-
Changes in Occlusion:
- Late mandibular growth can lead to changes in the occlusal relationship between the upper and lower teeth. This may result in the development of malocclusions or changes in existing malocclusions.
-
Facial Aesthetics:
- Continued growth of the mandible can affect facial aesthetics, including the profile and overall balance of the face. This may be particularly relevant in individuals with a retrognathic (recessed) mandible or those seeking cosmetic improvements.
-
Orthodontic Treatment Planning:
- Understanding the potential for late mandibular growth is crucial for orthodontists when planning treatment. It may influence the timing of interventions and the choice of appliances used to guide growth.
-
Surgical Considerations:
- In some cases, late mandibular growth may necessitate surgical intervention, particularly in adults with significant skeletal discrepancies. Orthognathic surgery may be considered to correct jaw relationships and improve function and aesthetics.
Monitoring Late Mandibular Growth
-
Clinical Evaluation:
- Regular clinical evaluations, including assessments of occlusion, facial symmetry, and growth patterns, are essential for monitoring late mandibular growth.
-
Radiographic Analysis:
- Cephalometric radiographs can be used to assess changes in mandibular growth and its relationship to the craniofacial complex. This information can guide treatment decisions.
-
Patient History:
- Gathering a comprehensive patient history, including growth patterns and any previous orthodontic treatment, can provide valuable insights into late mandibular growth.
| Concept | Detail |
|---|---|
| Cephalogram film distance | 15 cm |
| Most posterior point of foramen magnum | Opisthion |
| Smile for diagnosis | Posed smile |
| Duchenne smile | Unposed smile |
| Ricketts esthetic line | Pronasale to chin |
| Yaw | Left-right movement of maxilla |
| Point O | Sassouni analysis convergence point |
| ANB angle | Riedel |
| Steiner's chevrons | ANB with incisor positions |
| COGS cephalometrics | Burstone & Legan |
| Beta angle | Baik & Ververidou |
| Jarabak ratio 58% | Vertical growth pattern |
| Nasal length:width ratio | 70% |
| Morley's ratio | 75 – 100% (incisor visibility) |
| Golden proportion | Ricketts; value = 62% |
| Connector value (central-lateral) | 40% |
| Buccal corridor value | ~13% |
| Eva point | Medial stress line confluence (Ricketts) |
BONES OF THE SKULL
A) Bones of the cranial base:
A) Fontal (1)
B) Ethmoid (1)
C) Sphenoid (1)
D) Occipital (1)
B) Bones of the cranial vault:
1. Parietal (2)
2. Temporal (2)
C) Bones of the face:
Maxilla (2)
Mandible (1)
Nasal bone (2)
Lacrimal bone (2)
Zygomatic bone (2)
Palatine bone(2)
Infra nasal concha (2)
FUSION BETWEEN BONES
1. Syndesmosis: Membranous or ligamentus eg. Sutural point.
2. Synostosis: Bony union eg. symphysis menti.
3. Synchondrosis: Cartilaginous eg. sphenoccipital, spheno-ethmoidal.
GROWTH OF THE SKULL:
A) Cranium: 1. Base 2. Vault
B) Face: 1. Upper face 2.Lower face
CRANIAL BASE:
Cranial base grows at different cartilaginous suture. The cranial base may be divided into 3 areas.
1. The posterior part which extends from the occiput to the salatercica. The most important growth site spheno-occipital synchondrosis is situated here. It is active throughout the growing period and does not close until early adult life.
2. The middle portion extends from sella to foramen cecum and the sutural growth spheno-ethmoidal synchondrosis is situated here. The exact time of closing is not known but probably at the age of 7 years.
3. The anterior part is from foramen cecum and grows by surface deposition of bone in the frontal region and simultaneous development of frontal sinus.
CRANIAL VAULT:
The cranial vault grows as the brain grows. It is accelerated at infant. The growth is complete by 90% by the end of 5th year. At birth the sutures are wide sufficiently and become approximated during the 1st 2 years of life.
The development and extension of frontal sinus takes place particularly at the age of puberty and there is deposition of bone on the surfaces of cranial bone.
Growth is the increase in size It may also be defined as the normal change in the amount of living substance. eg. Growth is the quantitative aspect and measures in units of increase per unit of time.
Development
It is the progress towards maturity (Todd). Development may be defined as natural sequential series of events between fertilization of ovum and adult stage.
Maturation
It is a period of stabilization brought by growth and development.
CEPHALOCAUDAL GRADIENT OF GROWTH
This simply means that there is an axis of increased growth extending from the head towards feet. At about 3rd month of intrauterine life the head takes up about 50% of total body length. At this stage cranium is larger relative to face. In contrast the limbs are underdeveloped.
By the time of birth limbs and trunk have grown faster than head and the entire proportion of the body to the head has increased. These processes of growth continue till adult.
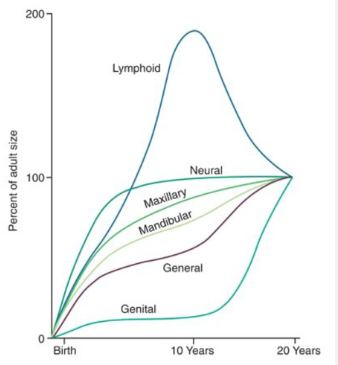
SCAMMON’S CURVE
In normal growth pattern all the tissue system of the body do not growth at the same rate. Scammon’s curve for growth shows 4 major tissue system of the body;
• Neural
• Lymphoid
• General: Bone, viscera, muscle.
• Genital
The graph indicates the growth of the neural tissue is complete by 6-7 year of age. General body tissue show an “S” shaped curve with showing of rate during childhood and acceleration at puberty. Lymphoid tissues proliferate to its maximum in late childhood and undergo involution. At the same time growth of the genital tissue accelerate rapidly.
| Class | Spacing | Crowding Risk in Permanent Dentition |
|---|---|---|
| I | Crowded | 10/10 |
| II | No spaces | 7/10 |
| III | 3 mm spacing | 5/10 |
| IV | 3 – 6 mm spacing | 2/10 |
| V | >6 mm spacing | None |